
What vertigo actually is
Vertigo is a specific sensation: the world spinning, or you spinning within it. That is different from light-headedness, feeling faint, or general unsteadiness — and the distinction genuinely matters, because each points towards a different set of causes.
True spinning vertigo usually originates in the inner ear balance organ, which is why it is an ENT problem. Light-headedness on standing more often relates to blood pressure. Unsteadiness without spinning may relate to vision, joints or neurological causes.
BPPV — the most common cause, and the most satisfying to treat
Benign paroxysmal positional vertigo accounts for a large share of vertigo cases. Tiny calcium crystals that normally sit in one part of the inner ear become dislodged into one of the semicircular canals. When you move your head, they shift and send a false signal of rotation.
The pattern is distinctive and worth recognising:
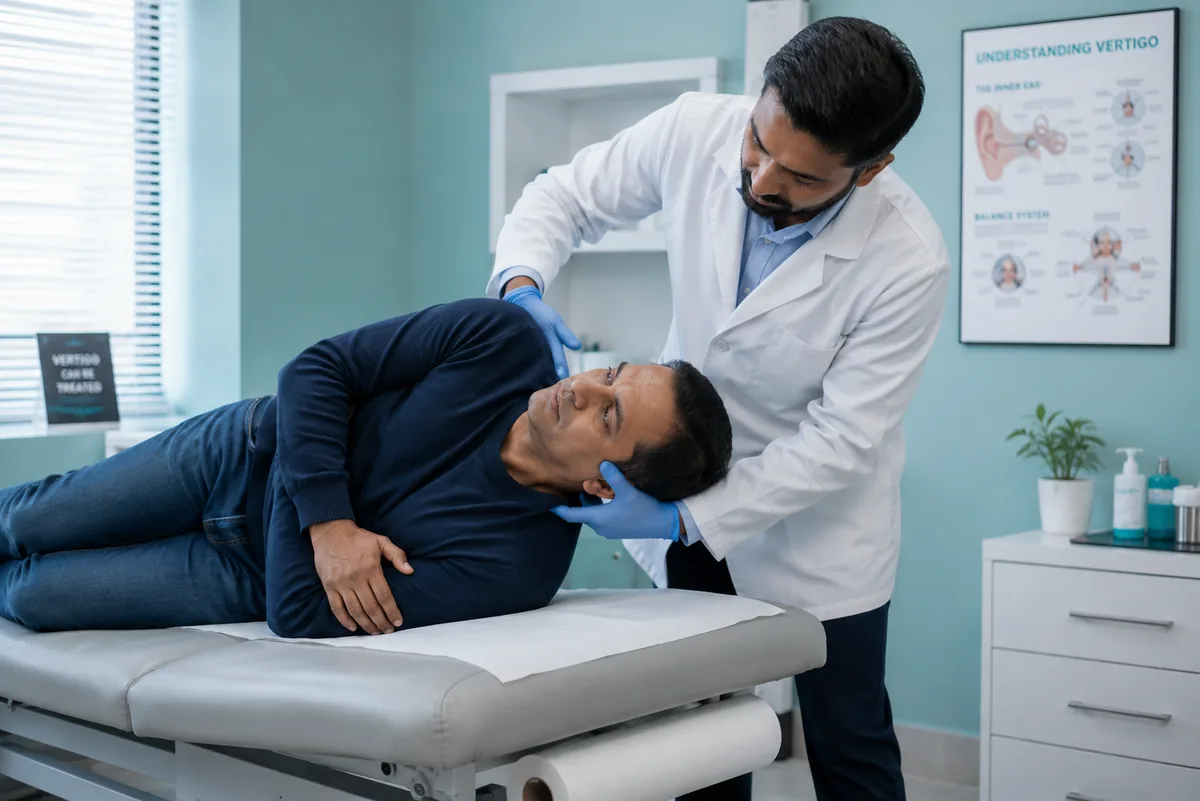
BPPV is diagnosed with a positional test — typically the Dix-Hallpike manoeuvre — where the specific eye movement pattern confirms which canal is involved. It is then treated with a repositioning manoeuvre such as the Epley, guiding the crystals back out of the canal.
Repositioning manoeuvres are highly effective for BPPV, and many patients walk out substantially better than they walked in. It can recur, and occasionally needs repeating, but this is one of the genuinely satisfying conditions in ENT — a mechanical problem with a mechanical solution, requiring no medication at all.
Other causes of vertigo
| Condition | Typical pattern | Hearing affected? |
|---|---|---|
| BPPV | Seconds, triggered by head position | No |
| Vestibular neuritis | Sudden, severe, constant for days | No |
| Labyrinthitis | Sudden, severe, lasting days | Yes |
| Ménière's disease | Episodes of 20 minutes to hours | Yes, fluctuating, with fullness and tinnitus |
| Vestibular migraine | Variable, often with headache or light sensitivity | Usually not |
Getting this classification right is most of the work. The duration of each episode and whether hearing is involved narrow the diagnosis considerably before any test is performed.
When dizziness needs urgent attention
Most vertigo is benign. These features are not, and warrant emergency assessment rather than a clinic appointment:
- Sudden severe headache alongside the dizziness
- Double vision, difficulty speaking or slurred speech
- Weakness or numbness of the face, arm or leg
- Inability to walk or stand at all
- Sudden hearing loss in one ear with vertigo
- Vertigo following a significant head injury
These can indicate a central cause involving the brain or its blood supply, and need immediate hospital assessment.
How vertigo is assessed
History does most of the diagnostic work here — how long each episode lasts, what triggers it, whether hearing changed, and what else accompanies it. Examination then includes:
- Positional testing such as Dix-Hallpike, to confirm BPPV and identify the affected canal.
- Examination for nystagmus — the involuntary eye movement pattern that distinguishes inner ear causes from central ones.
- Otoendoscopy to examine the ears, since middle ear disease can contribute.
- Hearing assessment, because whether hearing is affected substantially changes the diagnosis.
- Imaging, reserved for cases where a central cause is suspected or the picture is atypical.
Treatment
BPPV is treated with repositioning manoeuvres rather than drugs. Vestibular neuritis and labyrinthitis are managed with a short course of symptom relief followed by early vestibular rehabilitation — and here the instinct to rest is counterproductive.
Ménière's disease is managed with dietary salt reduction, diuretics and specific medication, with further options for resistant cases. Vestibular migraine responds to migraine management rather than to vertigo medication.
Vestibular suppressant medicines are useful for a few days in an acute attack. Taken for weeks, they actively prevent the brain from compensating for the inner ear problem — which is exactly the process that gets you better. Long-term use tends to prolong the imbalance rather than treat it.
Vestibular rehabilitation — structured exercises that retrain the balance system — is the mainstay for persistent imbalance and is more effective than medication for that phase.
Living with vertigo while you recover
Practical measures reduce risk during recovery: move from lying to sitting to standing in stages, keep a light on for night-time trips to the bathroom, remove loose rugs and trailing cables, avoid driving during active episodes, and stay hydrated. Falls are the main genuine danger, particularly in older patients.
The clinic is at Vatika Town Square, Sector 82A, with easy access from Kherki Daula, Manesar, Sohna Road and across New Gurugram.